
Obesity & Metabolic Surgery
Gastric Bypass Surgery in Antalya
Laparoscopic Roux-en-Y gastric bypass performed by Dr. Mani Habibi — a general surgeon with over 15 years of experience and more than 4,500 laparoscopic procedures.
Ask Dr. Habibi a Question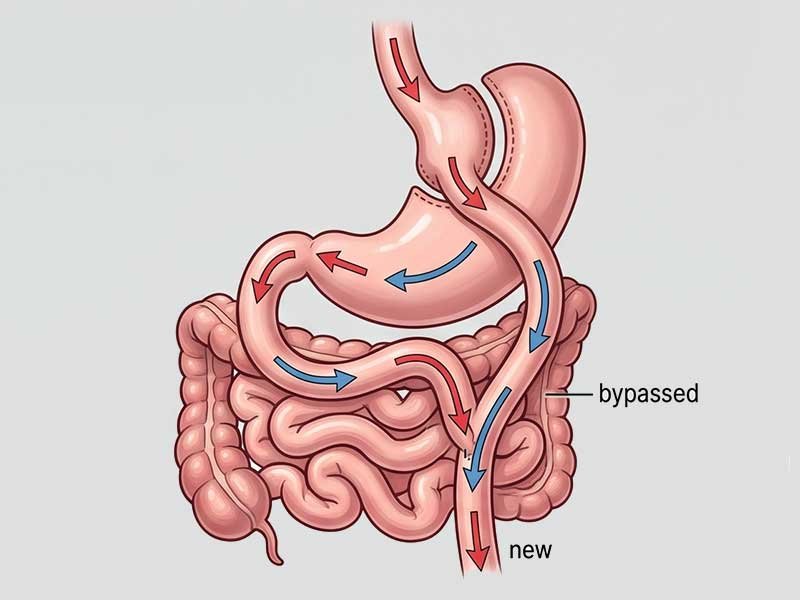
- Procedure
- Laparoscopic Roux-en-Y gastric bypass
- Anaesthesia
- General anaesthesia
- Operating time
- Approximately 90–150 minutes
- Hospital stay
- Usually 3–4 nights
- Return to work
- Typically 3–4 weeks
What is gastric bypass surgery?
Gastric bypass surgery, most commonly performed as Roux-en-Y gastric bypass, is a bariatric operation in which a small stomach pouch of roughly 30 ml is created and connected directly to the small intestine, bypassing the rest of the stomach and the first section of the intestine. It works in three ways: it limits how much can be eaten, reduces absorption of some calories and nutrients, and changes gut hormone signalling in a way that often improves type 2 diabetes. The procedure is performed laparoscopically through several small incisions.
Gastric bypass is one of the longest-established bariatric operations, with decades of published outcome data. Because it alters nutrient absorption by design, lifelong vitamin and mineral supplementation with regular blood monitoring is essential — a commitment every candidate must understand before surgery.
Who is a candidate for gastric bypass surgery?
Internationally accepted criteria generally consider bariatric surgery for adults who meet the following, after other weight-loss methods have been tried without lasting success:
- BMI of 40 or above, or
- BMI of 35–39.9 with an obesity-related condition such as type 2 diabetes, high blood pressure, sleep apnoea or joint disease
- In some cases, BMI of 30–34.9 with metabolic disease that is not controlled by other treatment
- Ability to undergo general anaesthesia, and readiness to commit to long-term dietary changes and follow-up
Gastric bypass is frequently the preferred option for patients with poorly controlled type 2 diabetes, significant gastro-oesophageal reflux, or a higher BMI, and for those needing revision after a previous sleeve gastrectomy. Eligibility is never determined online: Dr. Habibi assesses each patient individually through medical history, blood tests, endoscopy where indicated, and consultation with anaesthesia, dietetics and — where appropriate — psychology.
Important: Gastric bypass is a major operation, not a cosmetic procedure. It requires lifelong nutritional supplementation and follow-up, and works only alongside sustained changes in diet, physical activity and medical monitoring.
How is gastric bypass performed?
Pre-operative assessment
Blood tests, imaging, endoscopy where indicated, and consultations with anaesthesia and dietetics to confirm suitability.
Laparoscopic access
Under general anaesthesia, four to five incisions of about 1 cm are made in the abdomen for the camera and instruments.
Creating the pouch
A small stomach pouch of approximately 30 ml is created with surgical staplers and separated from the remainder of the stomach.
Rerouting and leak testing
The small intestine is divided and connected to the pouch, with a second connection restoring digestive juice flow. All joins are leak-tested before closure.
What does recovery look like?
What weight loss and diabetes outcomes can be expected?
Published outcomes commonly report an average loss of 65–80% of excess weight within the first 12–18 months after Roux-en-Y gastric bypass. Studies also report high rates of improvement or remission of type 2 diabetes, often within weeks of surgery and before major weight loss has occurred, reflecting the procedure's hormonal effects. Results vary considerably between individuals and depend heavily on dietary adherence, physical activity and follow-up. No surgeon can guarantee a specific outcome.
What are the risks and possible complications?
Like any major abdominal operation, sleeve gastrectomy carries risks. These should be discussed in detail during consultation:
- Early: bleeding, staple-line leak, infection, blood clots, reaction to anaesthesia
- Later: vitamin and mineral deficiencies (iron, B12, calcium, vitamin D), internal hernia, marginal ulcer, stricture at the join, gallstones
- Dietary: dumping syndrome after sugary or fatty meals; insufficient weight loss or weight regain in some patients
Nutritional deficiency deserves particular attention: because absorption is deliberately reduced, skipping supplements or follow-up blood tests after gastric bypass can lead to serious anaemia or neurological problems years later. This is a lifelong commitment, not a temporary one.
Gastric bypass or gastric sleeve?
| Aspect | Gastric Sleeve | Gastric Bypass |
|---|---|---|
| What is changed | Stomach reduced; intestines untouched | Stomach reduced and intestines rerouted |
| Nutrient absorption | Largely preserved | Partially reduced by design |
| Effect on reflux | May cause or worsen reflux | Often improves reflux |
| Diabetes remission | Frequently improves | Generally stronger metabolic effect |
| Reversibility | Not reversible | Technically reversible, rarely reversed |
| Often preferred for | Lower operative complexity, no reflux history | Higher BMI, type 2 diabetes, existing reflux |
Neither procedure is universally better. The right choice depends on BMI, metabolic conditions, reflux history, previous surgery and patient preference — determined together during consultation. Read more about gastric sleeve surgery.

General surgeon specialising in obesity and metabolic surgery in Antalya, Türkiye. Trained in bariatric surgery at the Cleveland Clinic (USA), recipient of the EAES Fellowship Award 2018, IFSO member, co-author of 40+ peer-reviewed publications. Full profile →
FAQ
Gastric bypass — frequently asked questions
How long does gastric bypass surgery take?
The operation usually takes about 90 to 150 minutes under general anaesthesia, depending on anatomy and whether it is a first or revisional procedure. Most patients stay in hospital for three to four nights.
Is gastric bypass reversible?
Technically yes — no stomach is removed, so the anatomy can be restored. In practice reversal is rarely performed and is reserved for serious complications such as severe malnutrition.
How much weight is lost after gastric bypass?
Published studies commonly report an average loss of 65–80% of excess weight within 12 to 18 months. Individual results vary widely and depend on diet, physical activity and long-term follow-up.
Will I need vitamin supplements for life after gastric bypass?
Yes, and this is more critical than after sleeve gastrectomy. Because part of the intestine is bypassed, absorption of iron, vitamin B12, calcium and vitamin D is reduced. Lifelong supplementation and regular blood tests are mandatory, not optional.
How long should international patients stay in Antalya?
Most international patients plan a stay of six to eight days for gastric bypass, allowing for pre-operative tests, surgery, recovery in hospital and a post-operative check before flying home. Flying is generally avoided in the first days after surgery because of the risk of blood clots.
What is dumping syndrome?
Dumping syndrome occurs when sugary or fatty food passes rapidly into the small intestine, causing nausea, cramping, sweating, palpitations or dizziness. It affects some patients after gastric bypass and is usually managed by avoiding refined sugar and eating smaller, slower meals.
Can gastric bypass help with reflux?
Yes. Roux-en-Y gastric bypass often improves gastro-oesophageal reflux, which is why it is frequently preferred for patients with significant reflux or a large hiatal hernia, and for those developing severe reflux after a sleeve gastrectomy.
Related Procedures
Other bariatric options
Is gastric bypass right for you?
Suitability can only be determined after a medical assessment. Send your questions and medical background — Dr. Habibi will review them personally.
Message on WhatsApp